Calcium: Food Sources, Bone Density, and What the Trials Found
In This Series: Nutrients
- Which Nutrients Are You Actually Short Of?
- How Nutrients Are Classified — and What the Reference Numbers Mean
- Vitamin A: Food Sources, Deficiency, and Safe Limits
- Vitamin C: Food Sources, Scurvy, and the Ceiling the Body Sets
- Vitamin D: Food Sources, Sunlight, and What the Trials Found
- Vitamin D2 vs D3: What the Head-to-Head Trials Found
- Riboflavin: Food Sources, Deficiency, and the Migraine Trials
- Thiamin: Food Sources, Beriberi, and Why There Is No Upper Limit
Key takeaways · 10 min read
- About 98 per cent of the body’s calcium is in bone, as hydroxyapatite: roughly 1,200 g in women and 1,400 in men. Blood calcium is defended by taking bone apart, so it does not report intake.
- Per tablespoon: poppy seed 216 mg, hard parmesan 177, whole sesame 146. Milk is last at 17, and milk is where most people get theirs.
- Whole sesame seeds carry 975 mg per 100 g; hulled ones, 60. The calcium is in the hull.
- Absorption falls as the dose rises: 36 per cent at 300 mg, 28 at 1,000, and highest at 500 mg or less.
In this article
- What it does
- The three foods that carry the most per spoonful
- How much of it gets in
- What a supplement does to bone
- And what it does to fractures
- The same evidence, read the other way
- The harm question, which has the same shape
- The numbers
- What the official pages say about calcium
- Questions people ask
- The short version
- Sources
Calcium has the widest gap in this series between how confidently it is recommended and what the trials of recommending it found. Two systematic reviews published in the same journal on the same day in 2015 pooled essentially the same evidence and concluded that increasing calcium intake does not prevent fractures. A meta-analysis from a major osteoporosis foundation, published the same year, reported hip fractures cut by 31 per cent.
Both are real papers and neither is fringe. This page is mostly about how that happened, because the mechanism underneath explains the disagreement better than either side does.
This is the first mineral entry in this appendix. It covers what calcium does, which foods carry it per measured spoonful, what running short does, and what the reference numbers are.
What it does
Calcium is structural before anything else. Roughly 98 per cent of the body’s calcium is stored in bone, and more than 99 per cent of that is calcium hydroxyapatite, an inorganic matrix. An adult carries about 1,200 grams if female and 1,400 if male, more than a kilogram of mineral held in a tissue that is continuously dismantled and rebuilt.
The remaining fraction, well under 2 per cent, does the signalling work of muscle contraction, nerve transmission and clotting. It is regulated tightly, and the skeleton is the buffer that keeps it steady. A blood calcium test therefore tells you almost nothing about intake, because the body will take bone apart to keep blood calcium where it belongs.
The three foods that carry the most per spoonful
Ranked by what fits on a level tablespoon, using USDA composition values:
Calcium per level tablespoon
USDA SR Legacy values per 100 g, converted at 15 g. Share is of the 1,000 mg adult RDA.
| Food (USDA FDC ID) | Per 100 g | Per tablespoon | Share of RDA |
|---|---|---|---|
| Poppy seed (171330) | 1,440 mg | 216 mg | 22% |
| Parmesan, hard (170848) | 1,180 mg | 177 mg | 18% |
| Sesame seeds, whole, dried (170150) | 975 mg | 146 mg | 15% |
| Tofu, firm, with calcium sulfate (172475) | 683 mg | 102 mg | 10% |
| Chia seeds, dried (170554) | 631 mg | 94.7 mg | 9% |
| Sardines, canned in oil, with bones (175139) | 382 mg | 57.3 mg | 6% |
| Milk, whole, with added vitamin D (171265) | 113 mg | 17 mg | 2% |
Source: USDA FoodData Central, SR Legacy. Tablespoon figures are conversions at 15 g.
Milk is last, at 17 mg a spoonful, and milk is the food everyone names. It earns its reputation by volume: a cup is 276 to 299 mg depending on fat content, and people drink cups. A tablespoon of poppy seed carries thirteen times as much calcium as a tablespoon of milk, and almost nobody gets their calcium from poppy seed.
One line in that table needs its own sentence. Whole sesame seeds carry 975 mg per 100 g, while hulled sesame seeds (the decorticated kernels, FDC 169412) carry 60. The calcium is in the hull, and hulling removes about 94 per cent of it. As with thiamin and rice bran, the nutrient sits in the fraction that processing takes off.
How much of it gets in
Calcium has a well-characterised and steep absorption curve, which is unusual in this series, and the shape of it matters more than any food table.
Fraction absorbed, by dose and by age
NIH Office of Dietary Supplements.
Two practical consequences follow without needing any trial. A single large tablet is the least efficient way to take calcium: the fraction absorbed falls as the dose rises, and the guidance to split doses at 500 mg describes the transporter and has no marketing origin. The body also compensates for low intake by absorbing a larger share of it, which is part of why adding more to an adequate diet does so little.
What a supplement does to bone
This number makes sense of everything else. A 2015 systematic review pooled 59 randomised trials of calcium intake with bone mineral density as the outcome.
Bone mineral density, pooled across 59 randomised trials
Percentage increase over one to more than two and a half years.
Source: Tai, V. et al., BMJ 351, 2015, h4183.
The increase arrives in year one and then stops, with no cumulative gain. There is also no dose-response: trials using 1,000 mg a day or more did not do better than trials using less, and people with the lowest baseline intakes did not gain more than people with the highest. That pattern is the opposite of what correcting a deficiency looks like.
Now put a number beside it. The average rate of bone density loss in older postmenopausal women is about 1 per cent a year, so increasing calcium intake buys back roughly one to two years of ordinary loss, once, and then slows that loss without stopping it. The reviewers’ own conclusion is that increases of this size are unlikely to translate into clinically meaningful reductions in fractures.
And what it does to fractures
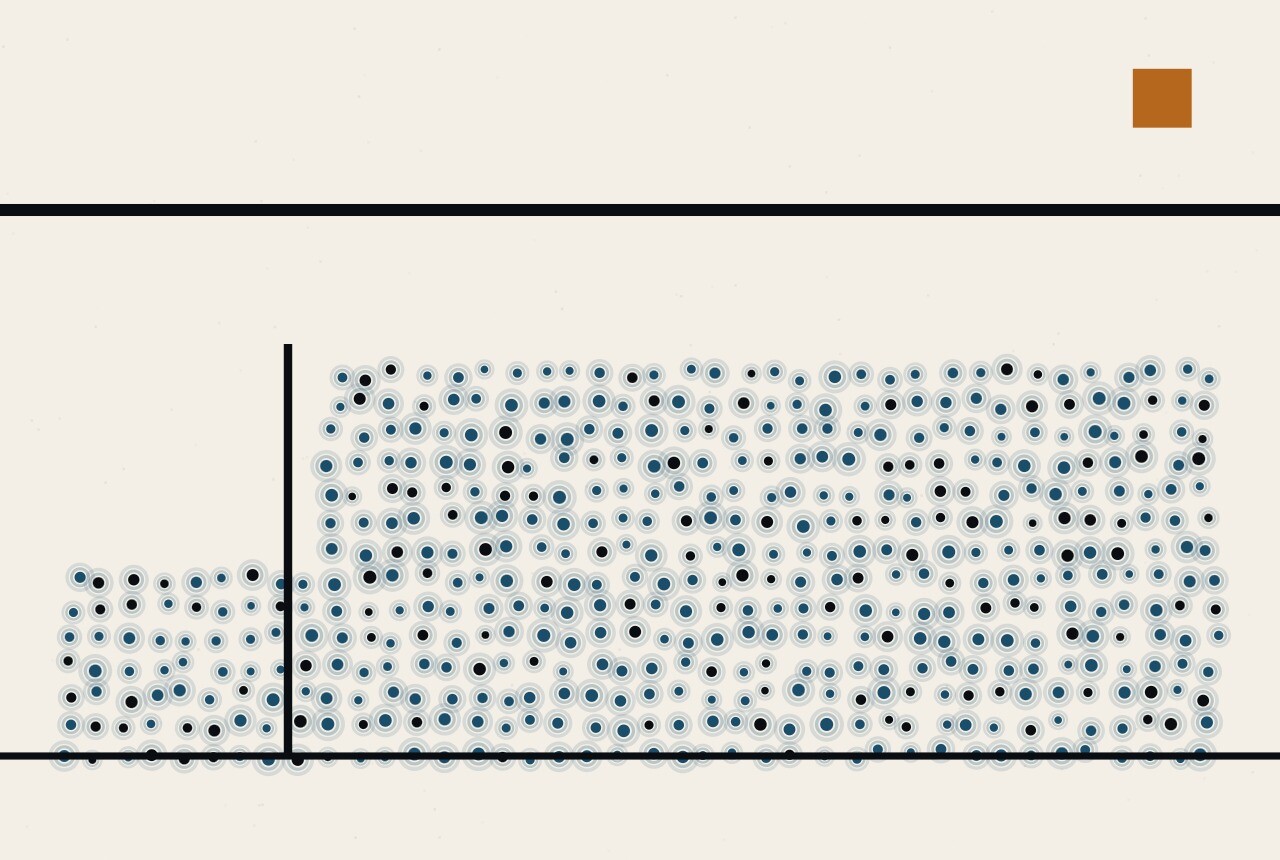
The companion review, published the same day, took fracture as the outcome, across 26 randomised trials and 69,107 participants.
Calcium supplements and fracture, pooled randomised trials
Relative risk. Below 1.00 favours supplementation.
Source: Bolland, M.J. et al., BMJ 351, 2015, h4580. Total fracture 95% CI 0.81 to 0.96; vertebral 0.74 to 1.00. Full bar = 25 per cent.
It found an 11 per cent reduction in total fracture and 14 per cent in vertebral, with nothing at the hip or forearm. Once the analysis was restricted to the trials at lowest risk of bias there was no reduction at any site, and there was evidence of publication bias among the small and moderate-sized studies. On dietary calcium the same review found 42 cohort studies, at least three quarters of which reported no association at all, and the two randomised trials of dietary sources between them enrolled 262 people.
The authors’ conclusion was blunt: clinicians, advocacy organisations and health policymakers should not recommend increasing calcium intake for fracture prevention, by supplement or by diet.
The same evidence, read the other way
In the same year, a meta-analysis from the National Osteoporosis Foundation pooled 11 trials of calcium plus vitamin D, with 52,915 participants, and reported total fractures down 16 per cent and hip fractures down 31 per cent, both statistically significant. The US Preventive Services Task Force, reviewing the field in 2018, landed in between: daily doses below 1,000 mg of calcium with less than 400 IU of vitamin D do not prevent fractures in postmenopausal women, and the evidence on larger doses is inadequate.
The disagreement turns on which trials belong in the pool (calcium alone or with vitamin D, community-dwelling or institutionalised, replete or deficient at baseline) and on how much weight to give the small positive studies that the funnel plots flag. Three groups made three defensible choices and got three answers, and none of them hid what they did.
The harm question, which has the same shape
The cardiovascular argument ran the same way and is still running.
Calcium supplements and cardiovascular risk: three readings
Each from randomised trial data.
The 2023 pooling does not refute the 2013 one so much as show how thin the data underneath both are: 219 myocardial infarctions spread across seven comparisons, and an interval running from a 12 per cent reduction to a 51 per cent increase. That result is a failure to resolve anything, and no null.
The kidney stone finding has a similar history. In the Women’s Health Initiative, 1,000 mg a day of supplemental calcium for seven years was linked to a greater risk of kidney stones, while two later systematic reviews of osteoporosis studies found no such association.
The numbers
The RDA is 1,000 mg a day for adults aged 19 to 50, rising to 1,200 for women over 50 and everyone over 70, and 1,300 for ages 9 to 18. The tolerable upper level is 2,500 mg for adults up to 70 and 2,000 mg above that.
Measured intakes sit close to those figures without a supplement: men over 20 average 1,083 mg a day from food and drink, and women 842. About 22 per cent of men and 32 per cent of women take a calcium supplement anyway. The shortfall is real and uneven: 39 per cent of everyone aged 4 and over takes in less than the estimated average requirement, and among children aged 4 to 18 it is 49 per cent.
What the official pages say about calcium
This section collects what US and UK government pages say about calcium intakes, food sources, supplements and what trials found for bones, hearts and kidney stones. It is general information, not medical advice; talk to a doctor before taking supplements.
| Source | What it says |
|---|---|
| NIH Office of Dietary Supplements, Calcium (health professional fact sheet) (update date not confirmed on the page) | RDA is 1,000 mg for ages 19–50, 1,200 mg for women 51–70 and everyone over 70, and 1,300 mg for ages 9–18. The upper limit is 2,500 mg for ages 19–50 and 2,000 mg from 51. Per serving: plain low-fat yogurt, 8 oz, 415 mg; calcium-fortified orange juice, 1 cup, 349; part-skim mozzarella, 1.5 oz, 333; canned sardines with bones, 3 oz, 325; nonfat milk, 1 cup, 299; firm tofu with calcium sulfate, half a cup, 253; cooked kale, 1 cup, 94; raw broccoli, half a cup, 21. |
| NIH ODS (same fact sheet), trial evidence | Fractures: one meta-analysis found 15% fewer total fractures and 30% fewer hip fractures with calcium plus vitamin D in older adults, while other reviews found no effect. Heart: one meta-analysis of 14 trials found 15% higher cardiovascular risk with calcium supplements, while an expert panel concluded intakes at or below the upper limit neither raise nor lower risk. Absorption is best at 500 mg or less per dose. |
| NIH ODS, Calcium (consumer fact sheet) (updated Sept. 14, 2023) | Says it is not clear whether calcium supplements help prevent fractures, and that some studies suggest supplements might raise heart risk. |
| US Preventive Services Task Force (an independent panel), vitamin D, calcium or combined supplementation to prevent fractures (Apr. 17, 2018; the page says it is being updated) | Recommends against supplementation with 400 IU or less of vitamin D and 1,000 mg or less of calcium to prevent fractures in postmenopausal women (grade D) and finds the evidence insufficient for men and premenopausal women. Combined supplementation increased kidney stones (relative risk 1.18). |
| NIH NIDDK, Eating, diet and nutrition for kidney stones (reviewed May 2017; old) | Says dietary calcium is not the cause of calcium stones and may block other stone-forming substances, and suggests getting calcium from food. It does not discuss supplements. |
| NHS, Calcium (reviewed Aug. 3, 2020; review overdue) and Osteoporosis prevention (reviewed Oct. 29, 2026) | Adults need 700 mg a day, and more than 1,500 mg a day may cause stomach pain and diarrhoea. Foods are listed without amounts. The osteoporosis page says to take a calcium supplement only if a doctor prescribes it. |
What we could not confirm: the US and UK adult figures differ widely (1,000–1,200 mg versus 700 mg) and neither page explains the gap, and the NHS names no formal upper limit while the US sets 2,000–2,500 mg. The kidney-stone evidence is described differently: ODS says its upper limit rests on observational data and two later reviews found no link, USPSTF reports more stones with combined supplements, and NIDDK says food calcium is not the cause. Heart findings are mixed. A separate NHS page for people over 65 says a calcium and vitamin D product may help if diet is lacking, which reads differently from the prescription-only line above, and it is itself past its review date. The USDA calcium table would not load, so food amounts come from ODS, and we did not confirm ODS’s own update date.
What to do
Steps sorted by when they matter. Each one says how strong the evidence is: Measured Official advice Untested
Before
- If your intake is low, get calcium from food first: yogurt, fortified plant milks, calcium-set tofu or whole sesame. Dietary and supplemental calcium raised bone density by the same small amount. Measured see Sources
- If you take a supplement, split it into doses of 500 mg or less. Absorption falls as the dose rises, from 36 per cent at 300 mg to 28 per cent at 1,000 mg. Measured see Sources
- Ask a doctor or pharmacist first if you have had kidney stones, take other bone treatment or take regular medicines. Calcium interacts with several of them. Official advice see Sources
What not to do
- Do not expect extra calcium on an adequate diet to keep building bone. Across 59 trials, bone density rose 1 to 2 per cent in the first year only. Measured see Sources
Not medical advice.
Who falls short on calcium: OECD countries by sex and age
OECD average, 38 countries (modelled estimate)
| Age group | Women | Men |
|---|---|---|
| Children 5–14 | 42% | 42% |
| Teens 15–19 | 51% | 46% |
| Adults 20–49 | 35% | 33% |
| Adults 50–64 | 34% | 31% |
| 65 and over | 36% | 33% |
Population-weighted share with usual intake below the average requirement, from food including current fortification, excluding supplements. These are modelled estimates built from national diet data; they can differ from what national surveys measure (see the next table).
What national surveys measured
| Country and survey | Teens F / M | Adults F / M | Older F / M |
|---|---|---|---|
| United StatesNHANES 2017–Mar 2020, USDA ARS · below EAR | 86% / 56%14–18 | 42% / 23%31–50 | 82% / 58%71+ |
| CanadaCCHS-Nutrition 2015, Health Canada · below EAR | 77% / 50%14–18 | 68% / 49%31–50 | 93% / 82%71+ |
| AustraliaNNPAS 2023, ABS · below EAR | 93% / 65%12–17 | 70% / 53%30–49 | 87% / 74%75+ |
| JapanMINNADE 2016–20 (Shinozaki et al. 2023) · below EAR | 71% / 58%15–17 | 78% / 82%30–49 | 37% / 50%65–74 |
| South KoreaKNHANES 2019–21 (Byeon et al. 2025) · below EAR | — | 79% / 72%19–69 | — |
| United KingdomNDNS 2019–23 · below LRNI (lower cut-off) | 18% / 15%11–18 | 10% / 9%19–64 | 8% / 5%65–74 |
| GermanyNVS II 2005–07, Max Rubner-Institut · below recommended intake (higher cut-off) | 74% / —14–18 | — | 65% / 61%65–80 |
“—” means not published or too unreliable to publish. Surveys differ in year, age bands, reference values and method, so compare countries as a rough guide. The UK’s LRNI is a lower cut-off than the EAR, so its percentages run lower. Supplements are excluded.
Where the model and the surveys disagree
- United States: the model estimates 7% of women and 6% of men aged 20–49, but NHANES 2017–Mar 2020, USDA ARS found 42% and 23% at 31–50. The two sources give different values.
- Canada: the model estimates 21% of women and 21% of men aged 20–49, but CCHS-Nutrition 2015, Health Canada found 68% and 49% at 31–50. The two sources give different values.
- Australia: the model estimates 48% of women and 40% of men aged 20–49, but NNPAS 2023, ABS found 70% and 53% at 30–49. The two sources give different values.
Why countries, sexes and ages differ
- Dairy is the main source in Western diets (about 72% of US calcium). In Japan 36% of men and 27% of women eat no dairy, and 78–79% of them fall short, against 34–37% of milk drinkers. (Saito et al., Nutrients 2019)
- Teenagers need more (1,300 mg in the US against 1,000 mg for adults) for bone building, which is why teen girls show the biggest shortfall almost everywhere. (NIH ODS, Calcium)
- Hard tap water can add a meaningful share: in one study, 2 litres a day of North American tap water gave 8–16% of the adult calcium reference intake. Food surveys usually leave tap water out; the global model assumes an average 46 mg per litre. (Azoulay et al., J Gen Intern Med 2001)
- UK flour must carry added calcium carbonate (235–390 mg per 100 g, rising from 13 December 2026), one reason UK intakes hold up. (GOV.UK, Bread and flour regulations)
- Why the model and surveys disagree: the model infers each country’s intake spread from median intakes, applies one harmonised set of requirements, and leaves out supplements (and, for some nutrients, fortification); surveys use national reference values and methods. (Passarelli et al., AJCN 2022)
Sources: Passarelli et al., Lancet Glob Health 2024; Global Datasets on Human Inadequate Nutrient Intakes (Harvard Dataverse, CC0, 2026; fortification from Friesen et al.); national surveys as linked in the table.
Questions people ask
How much calcium is in a tablespoon?
Poppy seed about 216 mg, hard parmesan 177, whole sesame seeds 146, calcium-set firm tofu 102, chia 94.7, sardines with bones 57.3, milk 17. Per serving the order inverts: a cup of low-fat yogurt is 415 mg, calcium-fortified orange juice 349, a cup of nonfat milk 299.
Should I take a calcium supplement?
If your intake is low, food is the better route, and serious people on both sides contest the trial evidence for supplements preventing fractures. If you take one anyway, the absorption data says to split it, because doses of 500 mg or less are absorbed most efficiently. Anyone with a history of kidney stones, or taking it alongside other treatment for bone, should have this conversation with a doctor.
Is dairy necessary?
No. Calcium-set tofu is 683 mg per 100 g, whole sesame 975, and fortified plant milks are matched to dairy by design: fortified soymilk is 299 mg a cup, the same as nonfat milk. The pooled review found dietary and supplemental calcium raised bone density by the same small amount, so the source matters less than the total.
Why do the studies disagree so much?
Because most of them enrolled people who already had enough. A supplement treats a shortage, and tested in the replete it produces the small, non-cumulative, non-dose-responsive bump the bone density review describes. Add publication bias among the small trials and different inclusion rules between review teams, and the same literature yields 31 per cent and zero.
The short version
- About 98 per cent of the body’s calcium is in bone, as hydroxyapatite: roughly 1,200 g in women and 1,400 in men. Blood calcium is defended by taking bone apart, so it does not report intake.
- Per tablespoon: poppy seed 216 mg, hard parmesan 177, whole sesame 146. Milk is last at 17, and milk is where most people get theirs.
- Whole sesame seeds carry 975 mg per 100 g; hulled ones, 60. The calcium is in the hull.
- Absorption falls as the dose rises: 36 per cent at 300 mg, 28 at 1,000, and highest at 500 mg or less.
- Across 59 trials, raising calcium intake lifts bone density 1 to 2 per cent, in the first year only, with no further gain. Ordinary loss after menopause is about 1 per cent a year.
- On fractures: 0.89 for total and 0.86 for vertebral across 26 trials, nothing at the hip, and nothing at all in the trials at lowest risk of bias. A foundation meta-analysis reported hip fractures down 31 per cent. Both were published in 2015.
This is a reference page, not clinical guidance. Calcium interacts with several common medications and with treatment for osteoporosis, and decisions about supplementing belong with a doctor or pharmacist.
Further reading: The two 2015 BMJ reviews are a matched pair and are best read together — the bone density one explains why the fracture one came out the way it did. Both are open access.
Sources
- NIH Office of Dietary Supplements, “Calcium”, fact sheet for health professionals. (RDA and UL tables; 98% of body calcium in bone; absorption 45% at 200 mg/day falling to 15% above 2,000, and 36% at a 300 mg supplement dose against 28% at 1,000; mean intakes 1,083 and 842 mg/day, with 39% of adults below the EAR; the cited cardiovascular and kidney stone findings; per-serving food figures.)
- USDA FoodData Central, SR Legacy, calcium per 100 g. (Poppy seed 171330, 1,440 mg; parmesan hard 170848, 1,180; sesame whole 170150, 975 against decorticated kernels 169412, 60; tofu with calcium sulfate 172475, 683; chia 170554, 631; sardines with bones 175139, 382; kale 168421, 254; whole milk 171265, 113.)
- Tai, V., Leung, W., Grey, A., Reid, I.R. and Bolland, M.J., “Calcium intake and bone mineral density”, BMJ 351, 2015, h4183. (59 randomised trials; dietary sources 0.6–1.8% and supplements 0.7–1.8%; present by one year with no further increase; no dose-response and no interaction with baseline intake.)
- Bolland, M.J., Leung, W., Tai, V., Bastin, S., Gamble, G. and Grey, A., “Calcium intake and risk of fracture”, BMJ 351, 2015, h4580. (26 trials, 69,107 participants; total fracture RR 0.89, 95% CI 0.81–0.96; vertebral 0.86, 0.74–1.00; hip 0.95, not significant; no reduction at any site in the trials at lowest risk of bias; publication bias among smaller trials.)
- Wallace, T.C. et al., National Osteoporosis Foundation meta-analysis, 2015. (11 studies, 52,915 participants; total fractures 0.84, 95% CI 0.73–0.96; hip 0.69, 0.56–0.86.)
- Kahwati, L.C. et al., evidence report for the US Preventive Services Task Force, JAMA, 2018, and the USPSTF conclusion on daily doses below 1,000 mg with under 400 IU vitamin D.
- Reid, I.R., “Cardiovascular effects of calcium supplements”, Nutrients 5(7), 2013. (Myocardial infarction up 27–31% and stroke 12–20% in pre-specified analyses of placebo-controlled trials.)
- Huo, X. et al., “Calcium supplements and risk of CVD”, Current Developments in Nutrition, 2023. (11 trials; calcium alone: MI RR 1.15, 95% CI 0.88–1.51 on 219 events; stroke 1.15, 0.90–1.46.)
- NIH ODS; NIH ODS consumer; USPSTF; NIDDK; NHS calcium; NHS osteoporosis.