
Running in the heat and heat stroke, and the cold-water tub where 274 of 274 survived
Key takeaways · 10 min read
- Exertional heat stroke is a core temperature above about 40°C with brain dysfunction; confusion is the key sign, and runners may still be sweating.
- It clusters in short, fast races and early-season heat: Falmouth’s 11.3 km race averaged 21 cases per 10,000 finishers, Boston 3.7 per 10,000 starters.
- Cool first, transport second: cold-water immersion brought all 274 Falmouth patients and all 26 at the Vermont City Marathon through alive.
- Most heat adaptation comes in the first four days of exposure; slowing down by heat flag and drinking to thirst, not to a schedule, also help.
On 19 April 2026 the temperature near the start of the DMZ Peace Marathon in Paju, South Korea, climbed towards 30°C. In Seoul, about 30 kilometres away, it reached 29.4°C, the highest mid-April reading since records began in 1907. Twelve runners fell ill with convulsions, dizziness or rapid breathing, and eight were taken to hospital, one of them to intensive care. Fire officials said the runners appeared to have pushed on as the heat rose.
Exertional heat stroke happens when a working body makes heat faster than it can shed it, and the brain begins to fail. It is one of the few sports emergencies with a treatment that works almost every time. Over 18 years at the Falmouth Road Race in Massachusetts, 274 runners with heat stroke were plunged into tubs of cold water at the finish. Every one of them survived.
This article covers what heat stroke does to a runner, why it clusters in short, fast races and early-season heat, and what has been measured to work, from cold-water immersion to heat flags and acclimatisation. The conclusion is not to stop running when it is warm. It is to run carefully and know what to do.
What heat stroke does to a runner
The American College of Sports Medicine defines exertional heat stroke as a rectal temperature above 40°C with signs of organ failure, most often in the brain. Above a critical point cells begin to be damaged. The ACSM stresses that it can strike seemingly healthy athletes even when the weather is relatively cool.
The key sign is a change in behaviour. Confusion, irrational answers, aggression, stumbling or collapse in a runner who has been working hard should be treated as heat stroke until proved otherwise. A hot, dry skin is not required: in one published case a runner who collapsed twice was found confused, incoherent and still sweating. Nurses at a Maine race warned in 2025 that patients can be combative.
How hot runners get
Core temperatures in degrees Celsius, measured rectally unless stated. Heat stroke is diagnosed on temperature together with brain dysfunction.
Sources: Sugawara et al., Frontiers in Sports and Active Living (2022); DeMartini et al., Medicine & Science in Sports & Exercise (2015); Lee et al., European Journal of Applied Physiology (2010), ingested sensor; Hosokawa et al., British Journal of Sports Medicine (2020).
Temperature alone does not make the diagnosis. In a Singapore study of 25 trained volunteers racing a half marathon at 26.4°C and 81% humidity, ten reached 40°C or more, and running speed was the strongest predictor of how hot they got. That is why medical teams look for the combination: a very high core temperature and a brain that is no longer working properly.
Where the risk concentrates
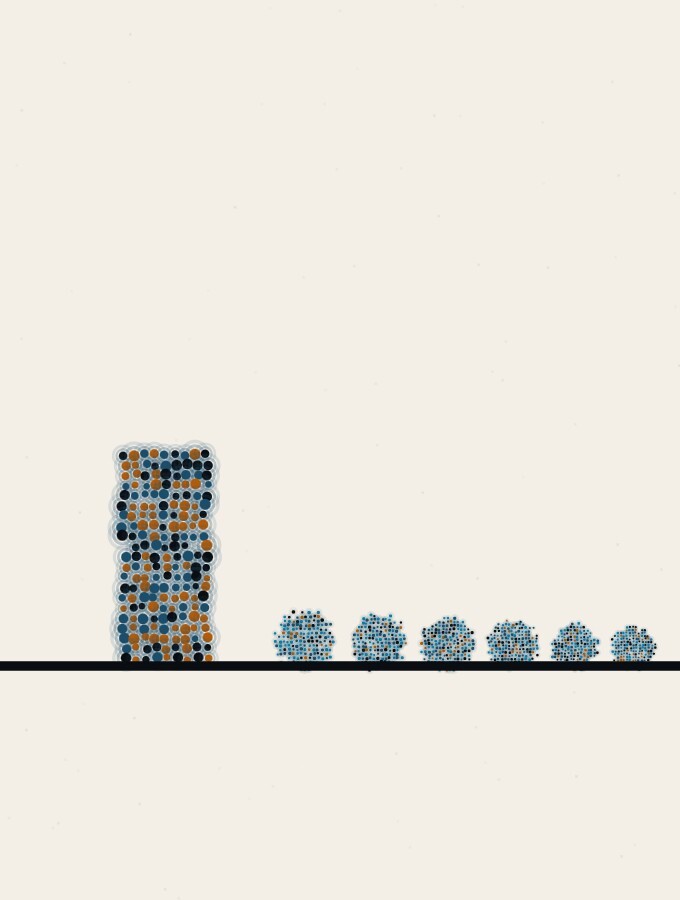
The surprise is that marathons are not the worst. The Falmouth Road Race is only 11.3 kilometres, but it is run in August and its runners can hold a hard pace from start to finish. Researchers reported that heat stroke there was about ten times as common as at other races. Of 393 heat illnesses treated over 18 years, 274, or 70%, were heat stroke, an average of 2.13 for every 1,000 finishers.
Pace mattered as much as weather. Among 100 runners with heat stroke at Falmouth between 2014 and 2018, the average pace was 5 minutes 35 seconds per kilometre, against 6 minutes 18 seconds for 53,369 other finishers, after allowing for age, sex, ability and conditions. Runners who collapsed did not slow down when the heat flags turned from yellow to red. At Boston, cases were linked with being under 30 and starting in the first two waves.
Heat stroke at four road races
Cases per 10,000 runners. Falmouth and Vermont City counts are per finisher or starter as reported; Boston per starter. Falmouth is 11.3 km, the others are marathons.
Sources: DeMartini et al., Journal of Athletic Training 49(4):478 (2014); Grundstein et al., Frontiers in Sports and Active Living (2019), year table; Brillhart et al., Clinical Journal of Sport Medicine (2025); Breslow et al., Medicine & Science in Sports & Exercise (2021).
The other concentration is in time. Heat that arrives before bodies have adapted is more dangerous than steady summer heat, which is why a hot April day in Korea or a warm late-May marathon in Vermont can fill a medical tent. In 13 Florida high schools, 94% of heat illnesses in American football came in the first 19 practices of the season. Among US service members, recruits in initial training had about 3.5 times the heat stroke rate of other enlisted personnel in 2025.
When and in whom heat illness concentrates
Relative rates from observational studies. A value above 1 means a higher rate than the comparison group.
Sources: Tripp et al., Orthopaedic Journal of Sports Medicine (2021); Armed Forces Health Surveillance Division, MSMR, May 2026; Belval et al., Journal of Athletic Training 55(12):1224 (2020).
Position statements add other risk factors: not being acclimatised, being dehydrated, having recently been ill, and taking certain medications. A 2020 systematic review offered a corrective, though. It found that primary evidence linking any single “known” factor directly to heat illness was not comprehensive, and that cases tended to appear when several factors combined, sometimes in weather that did not look hostile. Being fit and young is not protection; at Vermont the patients averaged 33, younger than the field.
What has been measured to work

The rule is cool first, transport second. Survival and complications depend on how long the body stays dangerously hot, so expert consensus asks for cooling to 39°C within 30 minutes of collapse. Heat stroke is one of the rare emergencies in which treatment on site comes before the ambulance. At Falmouth, the 274 patients arrived at an average of 41.4°C and cooled by 0.22°C a minute in cold water, reaching safety in roughly 11 minutes.
Immersion beats the alternatives because water draws heat away far faster than air. At the Vermont City Marathon, all 26 heat stroke patients were immersed and all survived; average time in the tub was 16 minutes, and since a protocol change in 2016 only 23% needed hospital transport. Where there is no tub, continuous dousing with cold water and ice massage still worked at the Marine Corps Marathon, though more slowly.
How fast different methods cool
Average fall in core temperature, °C per minute. Patients with heat stroke unless stated; rates depend on water temperature and starting temperature.
Sources: Hosokawa et al., BJSM (2020), citing Proulx et al.; DeMartini et al. (2015); Brillhart et al. (2025); McDermott et al., Aviation, Space, and Environmental Medicine (2009); Sugawara et al. (2022); Davis et al., MSSE abstract (2015).
Recognition depends on the right thermometer. External readings are unreliable in hot, sweating runners, so race medical teams use rectal probes. Practice still lags the evidence in places: a 2019 paper from Japanese researchers argued that rectal thermometry and whole-body immersion were not readily accepted outside sports and military medicine in Japan, before the Tokyo Olympics brought ice baths to the finish of the road events.
Prevention starts with the weather. Race medicine uses the wet bulb globe temperature, which combines heat, humidity, sun and wind. Under a scheme from the International Institute for Race Medicine, flags go yellow at 18°C, red at 23°C and black above 28°C, and ACSM guidance from 1996 set cancellation at about 28°C. A Minnesota analysis of the Twin Cities Marathon argued those limits were too permissive for unacclimatised amateurs.
Heat thresholds for races
Wet bulb globe temperature at the start, °C. Flags follow the International Institute for Race Medicine; the other lines come from marathon data.
Sources: Grundstein et al. (2019), flag categories; Roberts, Medicine & Science in Sports & Exercise 42(2):226 (2010), including ACSM 1996 and Chicago 2007 figures.
At the Twin Cities Marathon, heat stroke averaged none or one per race at a start temperature of about 13°C and 11 to 12 at about 22°C, so its medical director proposed not starting amateur fields above 20.5°C. At Chicago in 2007, with a start reading of 22.2°C, the race was halted midway; 185 runners went to hospital. Yet every Boston case from 2015 to 2019 happened on days averaging only 17°C to 20°C. Weather explains only part of the risk.
Acclimatisation is the runner’s own defence. A US Army review found that most adaptations to daily heat exposure, such as a lower core temperature and better sweating, appear in the first four days and are complete by about three weeks. In US high school football, players in states that fully followed national preseason acclimatisation guidelines were 55% less likely to suffer heat illness, after adjustment for August temperatures, according to researchers presenting 12 years of data.
Water is the trap on the other side. Drinking far more than is sweated out dilutes blood sodium, a condition called hyponatraemia that can also cause confusion and collapse, which is another reason to measure temperature before treating. In an 85-kilometre Tasmanian mountain run, those who drank to thirst drank less and finished with higher sodium than those following a set plan. After thirst-based education, only two of 130 Spanish trail and Ironman finishers ended up hyponatraemic.
Why the answer is not to stop running

Running is good for the heart, the mind and the bones, and as our article on running injuries explains, the long-feared damage to knees did not materialise in the data. Heat stroke is rare in absolute terms: even at Falmouth about two finishers in 1,000 are affected in an average year, and at Boston fewer than four in 10,000. When it is recognised and cooled at once, survival is close to 100%.
The habits are simple. Build up heat exposure in the days before a warm race. Run early, and slow down by flag rather than chasing a time. Skip the race after a fever or stomach bug. Drink to thirst. Run with someone who knows that confusion is the warning, and choose events with cold-water tubs at the finish. Organisers are adapting too: in March 2026, as heat was forecast, the Los Angeles Marathon let runners stop at 18 miles and still collect a medal, and nearly 1,000 did.
Questions people ask
What are the first signs of heat stroke while running?
Confusion is the key sign: odd answers, aggression, stumbling or collapse. A runner may still be sweating. Anyone who becomes confused during hard exercise in the heat should stop and be cooled.
What should I do if a runner collapses in the heat?
Call emergency services, then start cooling immediately. Immerse the body up to the neck in cold or iced water if possible, or douse continuously with cold water and ice while help arrives. Do not wait for an ambulance before cooling.
Can you get heat stroke when it is not very hot?
Yes. Hard running produces large amounts of heat, and cases have been recorded in mild weather, including every Boston case from 2015 to 2019.
How long does it take to acclimatise to heat?
Most adaptations develop in the first four days of daily heat exposure and are largely complete in about three weeks, according to US Army research. Build up gradually.
The short version
- Exertional heat stroke is a core temperature above about 40°C with brain dysfunction; confusion is the key sign, and runners may still be sweating.
- It clusters in short, fast races and early-season heat: Falmouth’s 11.3 km race averaged 21 cases per 10,000 finishers, Boston 3.7 per 10,000 starters.
- Cool first, transport second: cold-water immersion brought all 274 Falmouth patients and all 26 at the Vermont City Marathon through alive.
- Most heat adaptation comes in the first four days of exposure; slowing down by heat flag and drinking to thirst, not to a schedule, also help.
- Running in warm weather remains worthwhile. Acclimatise, run early, skip races when ill and pick events with cold-water tubs at the finish.
This is a summary of published research and reporting, not medical advice. Heat stroke is a medical emergency: if a runner is confused or collapses in the heat, call emergency services and start cooling immediately, ideally by immersion in cold water. If you have heart disease, take regular medication or have had heat illness before, talk to your doctor or physiotherapist before training or racing in hot weather.
Further reading: DeMartini et al., Medicine & Science in Sports & Exercise (2015), for 274 cooled runners and their survival. Roberts, Medicine & Science in Sports & Exercise (2010), for how a marathon set its do-not-start temperature. Roberts et al., Current Sports Medicine Reports (2021), the ACSM consensus on recognition and treatment.
- The Heat Will Kill You First, Jeff Goodell (2023). A journalist on what extreme heat does to bodies and places, with a vivid chapter on heat stroke. Wider than sport, and alarming in tone.
- Sweat: A History of Exercise, Bill Hayes (2022). A cultural history of exercise, from ancient gymnasia to modern running. Context rather than practical advice.
- The Art of Uncertainty, David Spiegelhalter (2024). A Cambridge statistician on chance and rare events. Helpful for reading rates per 10,000 runners without panic.
Sources
- Eight runners hospitalised after collapsing during South Korea marathon. Al Jazeera (AFP), 20 April 2026.
- Armstrong LE, Casa DJ, Millard-Stafford M, et al. American College of Sports Medicine position stand: exertional heat illness during training and competition. Medicine & Science in Sports & Exercise (2007), doi:10.1249/mss.0b013e31802fa199.
- Roberts WO, Armstrong LE, Sawka MN, et al. ACSM expert consensus statement on exertional heat illness: recognition, management, and return to activity. Current Sports Medicine Reports (2021), doi:10.1249/JSR.0000000000000878.
- Roberts WO, Dorman JC, Bergeron MF. Recurrent heat stroke in a runner: race simulation testing for return to activity. Medicine & Science in Sports & Exercise (2016), doi:10.1249/MSS.0000000000000847.
- Wight P. What happens to the body under extreme heat? Medical tent at Beach to Beacon offers a glimpse. Maine Public, 20 August 2025.
- Sugawara M, Manabe Y, Yamasawa F, Hosokawa Y. Athlete medical services at the marathon and race walking events during Tokyo 2020 Olympics. Frontiers in Sports and Active Living (2022), doi:10.3389/fspor.2022.872475.
- Lee JKW, Nio AQX, Lim CL, et al. Thermoregulation, pacing and fluid balance during mass participation distance running in a warm and humid environment. European Journal of Applied Physiology (2010), doi:10.1007/s00421-010-1405-y.
- Hosokawa Y, Casa DJ, Racinais S. Translating evidence-based practice to clinical practice in Tokyo 2020: how to diagnose and manage exertional heat stroke. British Journal of Sports Medicine (2020), doi:10.1136/bjsports-2020-102153.
- DeMartini JK, Casa DJ, Belval LN, et al. Environmental conditions and the occurrence of exertional heat illnesses and exertional heat stroke at the Falmouth Road Race. Journal of Athletic Training 49(4):478 (2014).
- DeMartini JK, Casa DJ, Stearns R, et al. Effectiveness of cold water immersion in the treatment of exertional heat stroke at the Falmouth Road Race. Medicine & Science in Sports & Exercise (2015), doi:10.1249/MSS.0000000000000409.
- Grundstein A, Hosokawa Y, Casa DJ, et al. Influence of race performance and environmental conditions on exertional heat stroke prevalence among runners participating in a warm weather road race. Frontiers in Sports and Active Living (2019), doi:10.3389/fspor.2019.00042.
- Breslow RG, Collins JE, Troyanos C, et al. Exertional heat stroke at the Boston Marathon: demographics and the environment. Medicine & Science in Sports & Exercise (2021), doi:10.1249/MSS.0000000000002652.
- Brillhart A, Dolbec K, Speck E, et al. Exertional heat stroke at the Vermont City Marathon, 2012 to 2023. Clinical Journal of Sport Medicine (2025), doi:10.1097/JSM.0000000000001367.
- Tripp BL, Winkelmann ZK, Eberman LE, Smith MS. Factors affecting incidence rate of exertional heat illnesses: analysis of 6 years of high school football practices in North Central Florida. Orthopaedic Journal of Sports Medicine (2021), doi:10.1177/23259671211026627.
- Armed Forces Health Surveillance Division. Update: heat exhaustion and heat stroke among U.S. active component service members, 2021–2025. MSMR, May 2026 (health.mil).
- Belval LN, Giersch GEW, Adams WM, et al. Age- and sex-based differences in exertional heat stroke incidence in a 7-mile road race. Journal of Athletic Training 55(12):1224 (2020).
- Westwood CS, Fallowfield JL, Delves SK, et al. Individual risk factors associated with exertional heat illness: a systematic review. Experimental Physiology (2020), doi:10.1113/EP088458.
- DeGroot DW, O’Connor FG, Roberts WO. Exertional heat stroke: an evidence based approach to clinical assessment and management. Experimental Physiology (2022), doi:10.1113/EP090488.
- McDermott BP, Casa DJ, O’Connor FG, et al. Cold-water dousing with ice massage to treat exertional heat stroke: a case series. Aviation, Space, and Environmental Medicine (2009), doi:10.3357/ASEM.2498.2009.
- Davis JK, Zhang Y, Casa DJ, Bishop P. Optimizing cold water immersion for exercise-induced hyperthermia. Medicine & Science in Sports & Exercise (2015), conference abstract, doi:10.1249/01.mss.0000477692.40016.8e; Zhang Y, et al., meta-analysis, doi:10.1249/MSS.0000000000000693.
- Pryor RR, Roth RN, Suyama J, Hostler DP. Exertional heat illness: emerging concepts and advances in prehospital care. Prehospital and Disaster Medicine (2015), doi:10.1017/S1049023X15004628.
- Hosokawa Y, Nagata T, Hasegawa M. Inconsistency in the standard of care: toward evidence-based management of exertional heat stroke. Frontiers in Physiology (2019), doi:10.3389/fphys.2019.00108.
- Roberts WO. Determining a “do not start” temperature for a marathon on the basis of adverse outcomes. Medicine & Science in Sports & Exercise 42(2):226–232 (2010).
- Sawka MN, Castellani JW, Pandolf KB, Young AJ. Human adaptations to heat and cold stress. US Army Research Institute of Environmental Medicine, DTIC ADP012427 (2002).
- High school football players in states that follow preseason guidelines less likely to suffer exertional heat illness. National Athletic Trainers’ Association press release on research by Kerr ZY et al.
- Scotney B, Reid S. Body weight, serum sodium levels, and renal function in an ultra-distance mountain run. Clinical Journal of Sport Medicine (2015), doi:10.1097/JSM.0000000000000131.
- López de Lara D, Ruiz-Sánchez JG, Cuesta M, et al. Exercise-induced hyponatremia: an assessment of the international hydration recommendations followed during the Gran Trail de Peñalara and Vitoria-Gasteiz Ironman competitions. Frontiers in Nutrition (2022), doi:10.3389/fnut.2021.781229.
- Krishna V. I treated heat stroke at the NYC Marathon. Marathons need to prepare for a climate-changed world. STAT (First Opinion), 2 October 2026.





