Magnesium food sources, and the limit that sits below the target
Key takeaways · 10 min read
- The 350 mg upper limit sits below the 420 mg RDA because it covers only supplements, where unabsorbed salts act as a laxative.
- 50–60% of body magnesium is in bone and under 1% is in serum, so a normal blood test cannot rule depletion out.
- Fractional absorption falls from about 65% at low intakes to 11% at high ones, and magnesium oxide measured about 4%.
- Ranked per tablespoon, the top foods are rice bran, dried basil and hulled hemp seed, and only the last is eaten by the spoon.
In this article
- How much magnesium you need a day
- What magnesium does, and where it actually sits
- The tablespoon table
- The measurement problem, stated plainly
- Why the dose on the bottle tells you so little
- Cramps: the clearest answer in the file, and the least quoted
- Where the evidence is thinner, but not zero
- Getting enough without a tablet
- What the official pages say about magnesium
- Questions people ask
- The short version
- Sources
Magnesium has an oddity in its reference values that is worth pausing on, because it is not a misprint and it is not an error. The recommended dietary allowance for an adult man aged 31 and over is 420 mg a day, while the tolerable upper intake level, the figure meant to mark where harm starts, is 350 mg. The ceiling sits below the target.
The two numbers measure different things. The 350 mg upper limit applies only to magnesium from supplements and medicines, and food magnesium is excluded. Magnesium salts that are not absorbed sit in the gut and draw water into it, which is why magnesium hydroxide is sold as a laxative. The upper limit is essentially a diarrhoea threshold and says nothing about a plate of food.
That distinction runs through the whole subject. Almost every practical question about magnesium, whether you are short of it, whether a supplement helps, which salt to buy, hits the same wall: the measurement everybody uses does not measure the compartment that matters.
How much magnesium you need a day
These are the US recommended dietary allowances (RDAs), the intake that covers nearly all healthy people in each group, and they count magnesium from food and supplements together. The separate 350 mg upper limit for adults covers supplements and medicines only, which is the oddity the rest of this article explains.
Magnesium RDA by age, milligrams a day
Food and supplements combined. Pregnancy and breastfeeding figures apply from age 14.
| Age | Men | Women | Pregnant | Breastfeeding |
|---|---|---|---|---|
| 1–3 | 80 | 80 | – | – |
| 4–8 | 130 | 130 | – | – |
| 9–13 | 240 | 240 | – | – |
| 14–18 | 410 | 360 | 400 | 360 |
| 19–30 | 400 | 310 | 350 | 310 |
| 31–50 | 420 | 320 | 360 | 320 |
| 51+ | 420 | 320 | – | – |
Source: NIH Office of Dietary Supplements, Magnesium fact sheet for health professionals (Table 1, from the Institute of Medicine Dietary Reference Intakes).
What magnesium does, and where it actually sits
Magnesium is a cofactor in several hundred enzyme reactions, and the most important of them is not exotic: the biologically active form of adenosine triphosphate, the cell’s energy currency, is magnesium-bound ATP. Magnesium also stabilises the structure of DNA and RNA, gates calcium channels, and is required for the enzyme that keeps potassium inside cells.
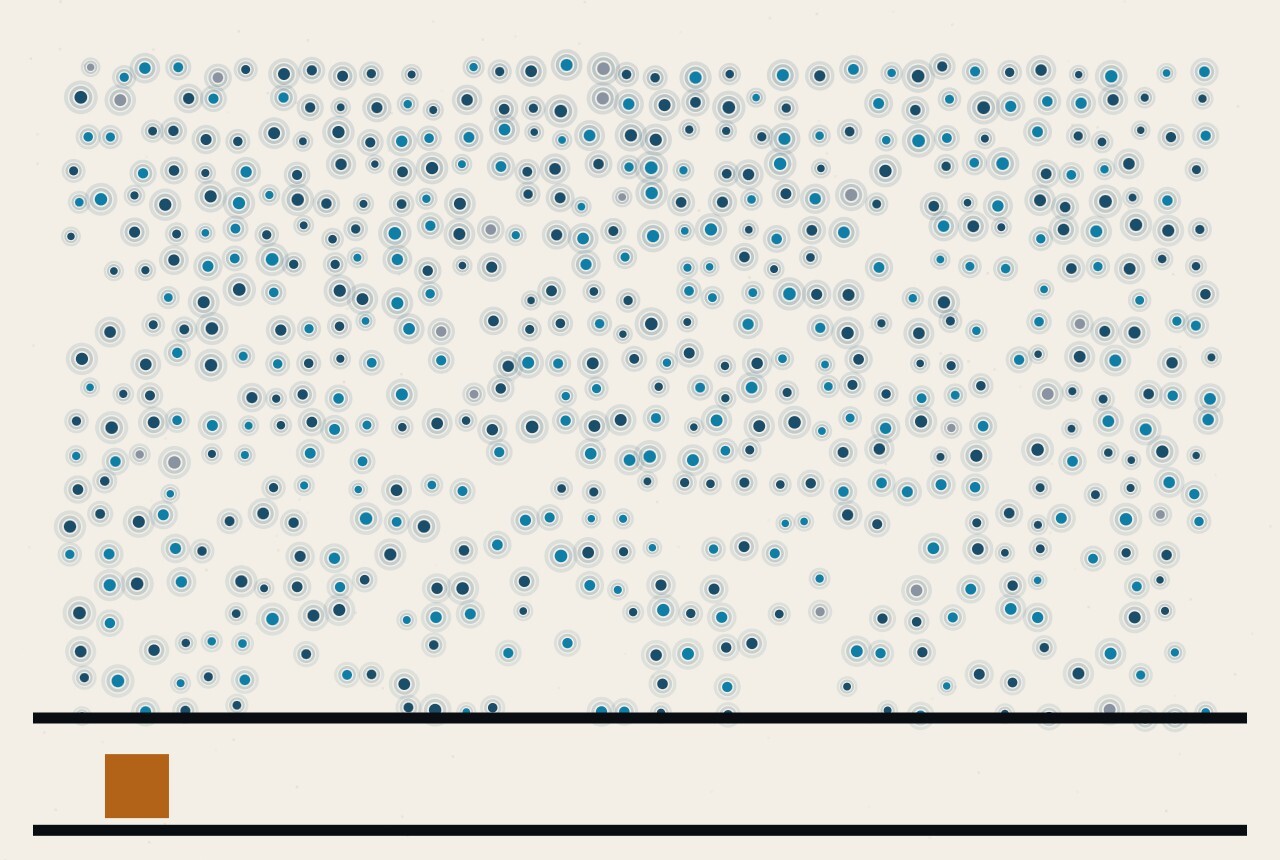
Its distribution makes it awkward to study. Between 50 and 60 per cent of the body’s magnesium is in bone, and most of the remainder is in soft tissue. Less than 1 per cent is in blood serum, a fraction the kidney defends by reabsorbing more when intake falls. A person can be meaningfully depleted in muscle and bone and still return a serum result inside the reference range.
Where the body keeps its magnesium
Source: NIH Office of Dietary Supplements, Magnesium fact sheet. The amber sliver is the part a routine blood test sees.
The tablespoon table
Measured by the spoon, magnesium behaves much like the other minerals in this series: the winners are dried, milled or pressed things that concentrate a plant into a small volume. Unlike iron, though, one of the top three is a food people genuinely eat by the spoonful.
Magnesium per level tablespoon (15 g)
USDA FoodData Central, SR Legacy. Values per 100 g, converted arithmetically to 15 g. An adult RDA is 310–420 mg.
| Food (FDC ID) | mg per 100 g | mg per 15 g | Share of a 420 mg RDA |
|---|---|---|---|
| Crude rice bran (169713) | 781 | 117 | 28% |
| Dried basil (171317) | 711 | 107 | 25% |
| Hulled hemp seed (170148) | 700 | 105 | 25% |
| Crude wheat bran (169722) | 611 | 91.7 | 22% |
| Pumpkin seed kernels (170556) | 592 | 88.8 | 21% |
| Unsweetened cocoa powder (169593) | 499 | 74.9 | 18% |
Source: USDA FoodData Central, SR Legacy entries as listed.
Three tablespoons of hemp seed is an ordinary portion and supplies about 315 mg, most of a day’s requirement. Rice bran and dried basil are the usual spoon-table illusions, since nobody eats 15 g of either. Cocoa powder is the interesting middle case: two tablespoons in a drink is normal and delivers about 150 mg.
The servings the NIH lists look tamer and are more useful: an ounce of pumpkin seeds at 156 mg, an ounce of almonds at 80 mg, half a cup of boiled spinach at 78 mg, half a cup of black beans at 60 mg, a medium banana at 32 mg. Magnesium is widely distributed and no single food is decisive, which is part of why shortfalls are quiet rather than dramatic.
The measurement problem, stated plainly
Roughly 48 per cent of Americans of all ages take in less magnesium from food and drink than the estimated average requirement for their age and sex, according to national survey modelling, with older men and adolescents most likely to fall short. That is a statement about intake arithmetic, not about anybody’s tissues.
The obvious next step, measuring it, does not work well. A systematic review of twenty candidate biomarkers of magnesium status concluded that only serum or plasma concentration, red cell concentration and urinary excretion clearly responded to dietary manipulation at all, and that the data were too thin to judge the rest. Serum is the one in routine use, and serum is the compartment holding under 1 per cent of the total.
This cuts both ways. A normal blood result is weak evidence that a person is replete. And supplementation trials that used serum magnesium as their endpoint may have been looking in the wrong place, an argument made at length in a 2026 review that reads the flat results in hypertension, insulin resistance, sleep, cramps and migraine as partly a problem of endpoint selection rather than of magnesium.
Why the dose on the bottle tells you so little
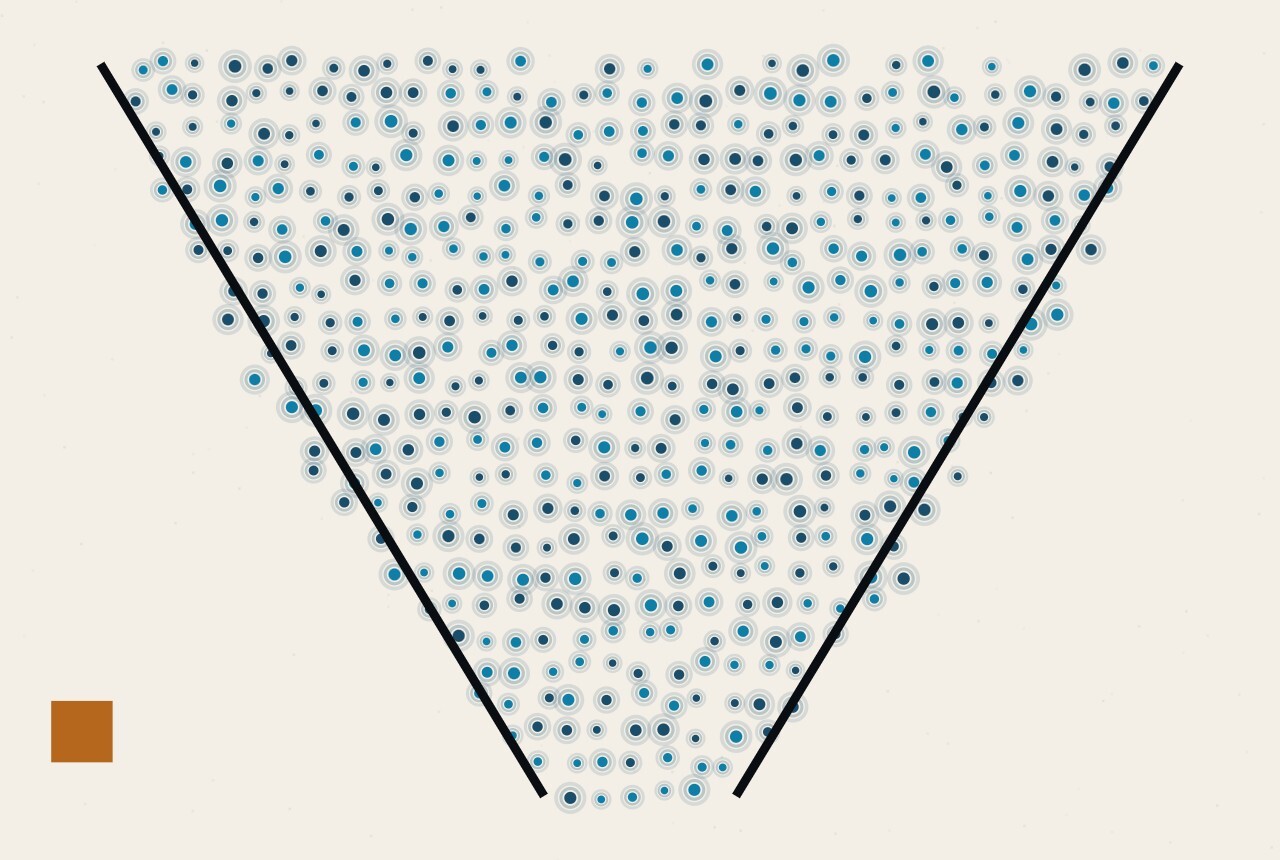
Fractional absorption falls steeply as the amount swallowed rises. The classic measurement, made in 1991 by perfusing normal subjects after a standard meal supplemented with graded doses of magnesium acetate, found it dropping from 65 per cent at the lowest intake to 11 per cent at the highest. The authors fitted the curve as a saturable mechanism plus a linear one that absorbs about 7 per cent of whatever is swallowed, without limit.
Fraction of ingested magnesium absorbed
Sources: Fine et al., J Clin Invest 88(2):396–402 (1991); NIH ODS; Firoz and Graber, Magnesium Research (2001).
The form matters too, though less than the marketing suggests. A comparison of four commercial preparations found magnesium oxide poorly absorbed at about 4 per cent, with chloride, lactate and aspartate substantially better and equivalent to each other. Oxide is the cheapest salt, the most common in bargain supplements and the one carrying the most elemental magnesium per tablet, which is how it ends up looking like good value on a label.
Together, those two facts explain the upper limit. Split doses of a well-absorbed salt get more magnesium in than one large dose of a poorly absorbed one, and the large dose of the poorly absorbed one is the version most likely to reach 350 mg and send you looking for a bathroom.
Cramps: the clearest answer in the file, and the least quoted
Magnesium is sold worldwide for muscle cramps, particularly to older people. A Cochrane review, updated to September 2019, pooled eleven randomised trials with 735 participants and reached one of the more definite conclusions in this subject area.
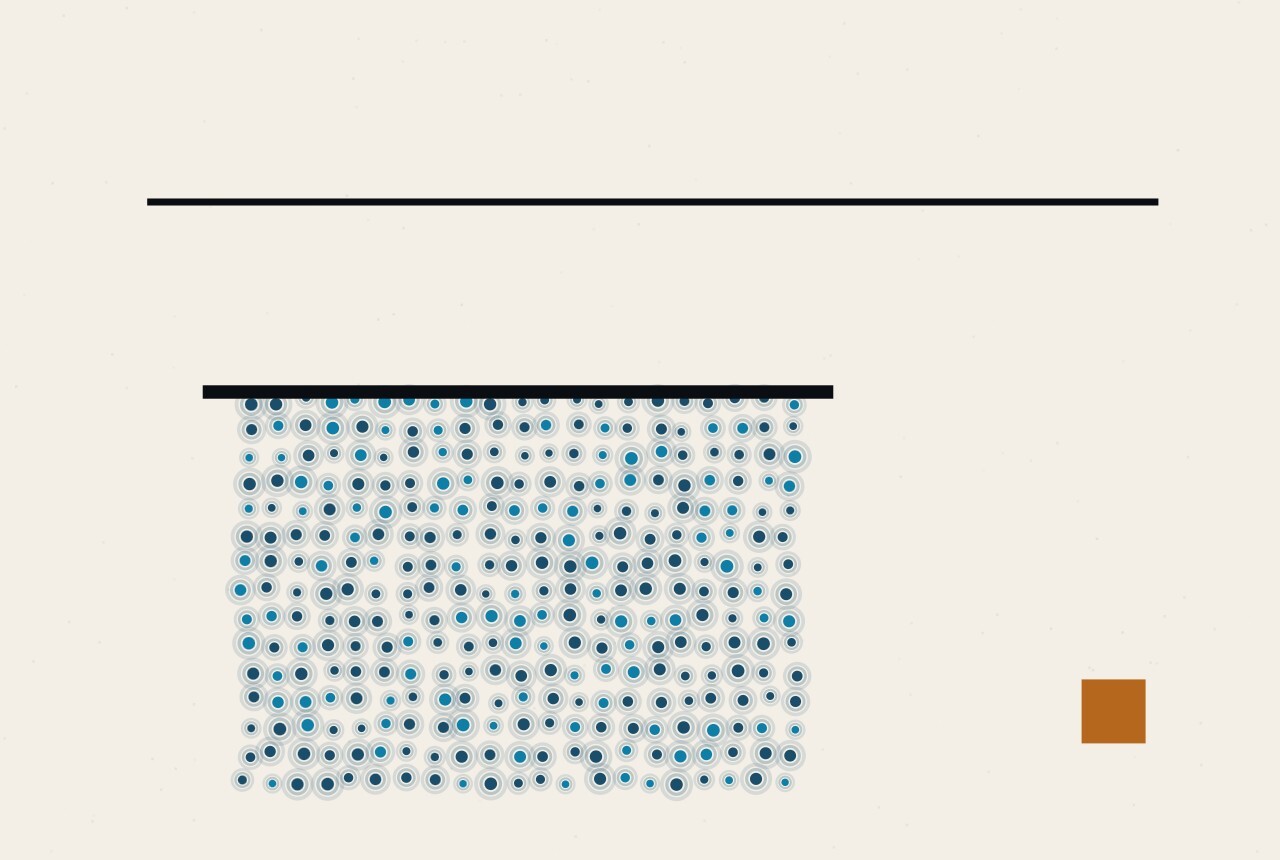
In older adults with idiopathic cramps, the change in cramps per week at four weeks was a mean difference of −9.59 per cent, with a confidence interval running from −23.14 to +3.97, moderate-certainty evidence that comfortably includes no effect. The proportion of people achieving at least a quarter fewer cramps had a relative risk of 1.04 (95% CI 0.84 to 1.29), which the reviewers graded high certainty. Minor side effects, mostly diarrhoea and nausea, appeared in 11 to 37 per cent of participants.
Magnesium for cramps, Cochrane 2020
Eleven trials, 735 people. Older adults with idiopathic cramps.
Source: Garrison et al., Cochrane Database of Systematic Reviews, CD009402.pub3 (2020).
The last line of that figure surprises people. For cramps during or after exercise, the use magnesium is most visibly marketed for, the reviewers found no randomised controlled trials at all. Not negative trials. None. In pregnancy the picture is genuinely unresolved: the trials disagreed too much to be combined, and the certainty was rated very low.
Where the evidence is thinner, but not zero
Three areas deserve separating from the cramp result, because they are weaker in a different way: small real effects rather than clear absence.
Three claims, three kinds of evidence
Source: NIH Office of Dietary Supplements, Magnesium — Health Professional Fact Sheet.
Bone is a fourth case and the most frustrating. Half the body’s magnesium is in the skeleton, and population studies find associations between magnesium intake and bone mineral density in both sexes, yet there is no trial base worth the name. Plausibility and correlation have sat together for thirty years without an adequate randomised test.
Getting enough without a tablet
The dietary route is unglamorous because it has no single hero food: whole grains rather than refined, legumes, nuts and seeds, leafy greens, and cocoa. Refining strips magnesium out. The bran that holds 611 mg per 100 g is the part removed to make white flour, and unlike iron, magnesium is not added back by enrichment. Milling tells a quieter version of the same story about the B vitamins.
Some groups have a real reason to look harder: people with Crohn’s disease or coeliac disease, people with type 2 diabetes, who lose more in urine, people with chronic alcohol dependence, and older adults, who absorb less and excrete more. Some common medicines matter too, particularly long-term proton pump inhibitors and loop or thiazide diuretics.
For anyone else, the intake statistics suggest a widespread shortfall, the blood test cannot confirm it, and the trials of correcting it have mostly produced small effects. That is where the evidence stands.
What the official pages say about magnesium
This section sets side by side what US, UK and EU official pages say about magnesium amounts, supplement ceilings and the claims about cramps, blood pressure and migraine. It is general information, not medical advice; check with a doctor or pharmacist, especially if you take diuretics, antibiotics or osteoporosis medicines.
| Source | What it says |
|---|---|
| NIH Office of Dietary Supplements (US government), Magnesium fact sheet for health professionals (updated Jan. 6, 2026) | RDA in mg a day: men 400 (ages 19–30) and 420 (31 and over); women 310 and 320; pregnancy 350 at 19–30 and 360 at 31–50. The upper limit is 350 mg a day and applies only to magnesium from supplements and medicines, not to magnesium naturally in food. |
| NIH ODS (same page), foods | Per serving: roasted pumpkin seeds (1 oz) 156 mg, chia seeds (1 oz) 111 mg, almonds (1 oz) 80 mg, boiled spinach (half cup) 78 mg, cashews (1 oz) 74 mg, black beans (half cup) 60 mg. |
| NIH ODS (same page), claims | Leg cramps appear only as a symptom of worsening deficiency, not as something the page recommends magnesium to treat. For blood pressure the effect is small: a Cochrane review found about a 2.2 mmHg diastolic drop, and the FDA’s 2022 qualified health claim calls the evidence inconsistent and inconclusive. For type 2 diabetes the American Diabetes Association (a non-government body) is quoted as saying evidence is insufficient. For migraine, the American Academy of Neurology and American Headache Society (both non-government) rate it “probably effective,” but typical preventive doses exceed the upper limit, so it needs clinical supervision. |
| NIH ODS (same page), medicines | Separate magnesium from oral bisphosphonates by at least 2 hours. Take tetracycline or quinolone antibiotics at least 2 hours before, or 4–6 hours after, magnesium. Loop and thiazide diuretics raise magnesium loss in urine; long-term proton pump inhibitors (over about a year) can lower blood magnesium. |
| NHS (UK government), Vitamins and minerals: others (magnesium section) (last reviewed Aug. 3, 2020; review was due Aug. 2023) | Adults 19–64: 300 mg a day for men, 270 mg for women. Supplements of 400 mg a day or less are unlikely to cause harm; more than that for a short time may cause diarrhoea, and the page says there is not enough evidence on long-term high doses. The page is past its own review date. |
| EFSA (EU agency), Dietary reference values for magnesium (EFSA Journal, 2015) | Adequate intake 350 mg a day for men and 300 mg for women. No upper limit appears on this page. |
| EFSA (EU agency), Opinion that states a magnesium upper limit (no date shown on the page read) | States an upper limit of 250 mg a day for supplemental magnesium. The page did not say which committee or earlier opinion set that figure. |
| Our comparison | The supplement ceilings differ: 350 mg (US upper limit), 400 mg (NHS “unlikely to cause harm,” which is not a formal upper limit) and 250 mg (EFSA). The target intakes differ too, and the US RDA, the EFSA adequate intake and the NHS reference amounts are different kinds of figure, so they are not strictly comparable. |
We could not confirm the NHS’s own dedicated magnesium page (only the older combined page above was read), where the EFSA 250 mg limit originally came from or when, or any official page recommending magnesium for leg cramps. Figures were read through automated page fetches, so confirm exact numbers on the live pages.
What to do
Steps sorted by when they matter. Each one says how strong the evidence is: Measured Official advice Untested
Before
- Get magnesium from food. The 350 mg upper limit applies only to supplements and medicines, where unabsorbed salts act as a laxative. Official advice see Sources
- If you buy a supplement, avoid magnesium oxide. It measured about 4% absorption. Measured see Sources
- Ask a clinician first if you have kidney impairment or take regular medicines. Magnesium supplements are not safe at ordinary doses when the kidney cannot clear a surplus. Official advice see Sources
What not to do
- Do not take magnesium for night-time leg cramps in older age. Pooled trials found no benefit, with the clearest outcome graded high certainty. Measured see Sources
Not medical advice and not a reason to start or stop a supplement.
Who falls short on magnesium: OECD countries by sex and age
OECD average, 38 countries (modelled estimate)
| Age group | Women | Men |
|---|---|---|
| Children 5–14 | 14% | 14% |
| Teens 15–19 | 57% | 62% |
| Adults 20–49 | 33% | 54% |
| Adults 50–64 | 33% | 54% |
| 65 and over | 38% | 59% |
Population-weighted share with usual intake below the average requirement, from food only (fortification not modelled), excluding supplements. These are modelled estimates built from national diet data; they can differ from what national surveys measure (see the next table).
What national surveys measured
| Country and survey | Teens F / M | Adults F / M | Older F / M |
|---|---|---|---|
| United StatesNHANES 2017–Mar 2020, USDA ARS · below EAR | 89% / 81%14–18 | 49% / 55%31–50 | 59% / 61%71+ |
| CanadaCCHS-Nutrition 2015, Health Canada · below EAR | 73% / 53%14–18 | 45% / 54%31–50 | 64% / 75%71+ |
| AustraliaAHS 2011–12, ABS · below EAR | 72% / 61%14–18 | 33% / 36%31–50 | 49% / 64%71+ |
| JapanMINNADE 2016–20 (Shinozaki et al. 2023) · below EAR | 79% / 48%15–17 | 58% / 81%30–49 | 14% / 32%65–74 |
| South KoreaKNHANES 2021 (KDCA, Park et al. 2023) · below EAR | 74% / 58%12–18 | 48% / 46%30–49 | 47% / 47%65+ |
| United KingdomNDNS 2019–23 · below LRNI (lower cut-off) | 48% / 31%11–18 | 15% / 20%19–64 | 9% / 11%65–74 |
“—” means not published or too unreliable to publish. Surveys differ in year, age bands, reference values and method, so compare countries as a rough guide. The UK’s LRNI is a lower cut-off than the EAR, so its percentages run lower. Supplements are excluded.
Where the model and the surveys disagree
- United States: the model estimates 26% of women and 54% of men aged 20–49, but NHANES 2017–Mar 2020, USDA ARS found 49% and 55% at 31–50. The two sources give different values.
- Canada: the model estimates 17% of women and 41% of men aged 20–49, but CCHS-Nutrition 2015, Health Canada found 45% and 54% at 31–50. The two sources give different values.
- Japan: the model estimates 83% of women and 98% of men aged 20–49, but MINNADE 2016–20 (Shinozaki et al. 2023) found 58% and 81% at 30–49. The two sources give different values.
Why countries, sexes and ages differ
- Refining grain strips most magnesium: half a cup of brown rice has 42 mg, white rice 10 mg. Men need more (400–420 mg), which fits men’s higher shortfall. (NIH ODS, Magnesium)
- Tap water ranges from about 1 to over 120 mg per litre. Two litres of some North American tap waters supplied 6–31% of the adult magnesium reference intake, and WHO notes that very few intake studies count drinking and cooking water. (WHO, Calcium and magnesium in drinking-water (2009))
- Why the model and surveys disagree: the model infers each country’s intake spread from median intakes, applies one harmonised set of requirements, and leaves out supplements (and, for some nutrients, fortification); surveys use national reference values and methods. (Passarelli et al., AJCN 2022)
Sources: Passarelli et al., Lancet Glob Health 2024; Global Datasets on Human Inadequate Nutrient Intakes (Harvard Dataverse, CC0, 2026; fortification from Friesen et al.); national surveys as linked in the table.
Questions people ask
If my blood magnesium is normal, am I fine?
It is weak reassurance and not proof. Serum holds under 1 per cent of body magnesium and the kidney defends that fraction, so a normal result is compatible with depleted tissue. It remains the test in routine use because the alternatives are not better validated.
Which magnesium salt should I buy?
The published comparison found oxide absorbed at around 4 per cent against substantially better and roughly equal figures for chloride, lactate and aspartate. That study was small and used urinary increment rather than isotopes, so it supports avoiding oxide but does not rank the rest.
Will magnesium stop my leg cramps at night?
The pooled randomised evidence in older adults says probably not, and that finding is graded high certainty for the clearest outcome measure. It is one of the few places in nutrition where the answer is reasonably settled.
Why is the upper limit lower than the recommended intake?
Because they describe different things. The 350 mg limit is a threshold for the laxative effect of unabsorbed magnesium salts from supplements and medicines, and food magnesium is outside it. In people with normal renal function the kidney handles dietary surpluses without difficulty.
Does magnesium help with sleep?
The trials are small and mostly used serum as a status check rather than a proper endpoint. There is not enough there to call it either way, which is a different statement from the cramp result.
The short version
- The 350 mg upper limit sits below the 420 mg RDA because it covers only supplements, where unabsorbed salts act as a laxative.
- 50–60% of body magnesium is in bone and under 1% is in serum, so a normal blood test cannot rule depletion out.
- Fractional absorption falls from about 65% at low intakes to 11% at high ones, and magnesium oxide measured about 4%.
- Ranked per tablespoon, the top foods are rice bran, dried basil and hulled hemp seed, and only the last is eaten by the spoon.
- For cramps in older adults, pooled trials found no benefit, with the clearest outcome graded high certainty; for exercise cramps there are no trials at all.
- Blood pressure, diabetes and migraine show small or observational effects, and bone has plausibility without a trial base.
This describes what published research has reported. It is not medical advice and not a reason to start or stop a supplement. Magnesium supplements interact with several common medicines and are not safe at ordinary doses in significant kidney impairment, where the kidney cannot clear a surplus — that is a conversation with a clinician, not a label.
Further reading: Fine et al., Journal of Clinical Investigation 88(2):396–402 (1991), for the absorption curve. Garrison et al., Cochrane Database of Systematic Reviews CD009402.pub3 (2020), for the cramp review. Witkowski et al., Magnesium Research 24(4):163–180 (2011), for the survey of status biomarkers.
Sources
NIH Office of Dietary Supplements, Magnesium — Health Professional Fact Sheet (RDAs, the 350 mg UL and its scope, distribution between bone, soft tissue and serum, 30–40% typical absorption, NHANES shortfall, food servings, blood pressure, diabetes, osteoporosis and migraine sections, laxative effect).
USDA FoodData Central, SR Legacy: 169713, 171317, 170148, 169722, 170556, 169593, 170567, 168462, 173734.
Fine KD, Santa Ana CA, Porter JL, Fordtran JS. Intestinal absorption of magnesium from food and supplements. J Clin Invest 1991;88(2):396–402.
Firoz M, Graber M. Bioavailability of US commercial magnesium preparations. Magnesium Research 2001 (PMID 11794633).
Garrison SR, Korownyk CS, Kolber MR, et al. Magnesium for skeletal muscle cramps. Cochrane Database Syst Rev 2020;9:CD009402.
Witkowski M, Hubert J, Mazur A. Methods of assessment of magnesium status in humans: a systematic review. Magnes Res 2011;24(4):163–180.
Chandarana J, Butani K. Why serum magnesium fails: a narrative review of magnesium biochemistry, compartmental exchange, and endpoint selection for supplementation trials. J Am Nutr Assoc 2026 (online).