Rock climbing injuries, fingers, falls and the rope
Key takeaways · 9 min read
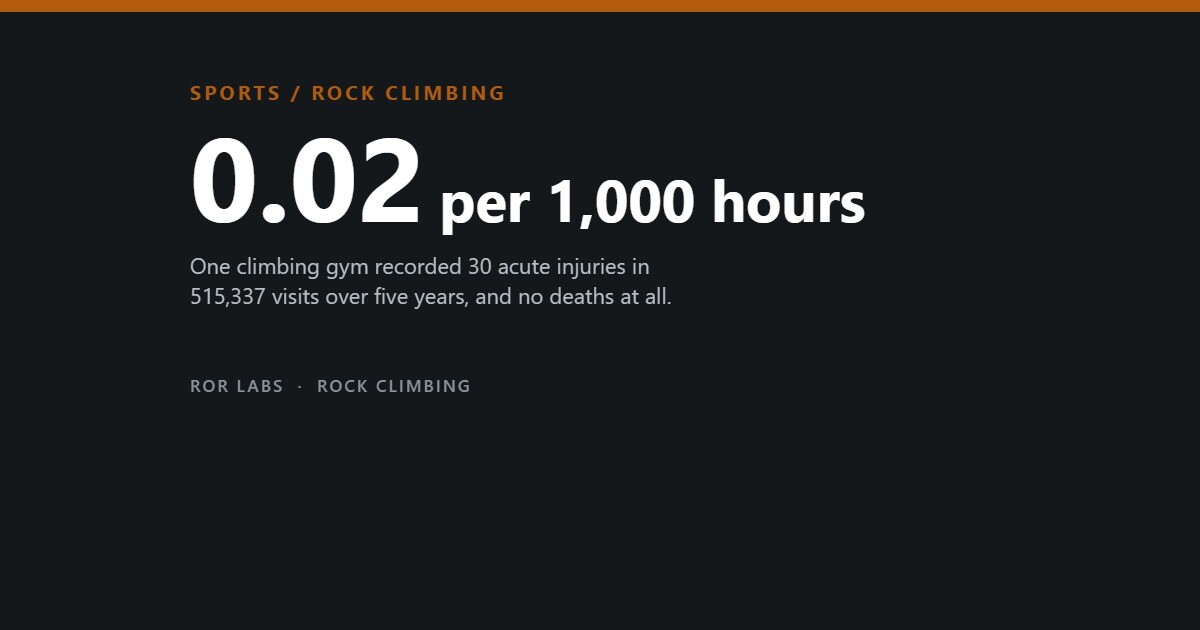
- A climbing gym recorded 0.02 acute injuries per 1,000 hours; counting overuse raises the rate to 2 to 4.
- Finger pulley injuries make up about a fifth of climbing injuries; most are overuse.
- Bouldering causes most gym accidents, mainly ankles from falls onto mats.
- Serious accidents outdoors turn on the rope system and on helmets: no helmet, 1.81 times the odds of severe injury.
A German climbing gym recorded 515,337 visits over five years and counted 30 acute injuries in that time. Nobody died. The researchers worked out a rate of 0.02 injuries per 1,000 hours of climbing, lower than almost any sport in this series.
Climbing’s reputation comes from somewhere else: the cliff, the long fall, the rope that was too short. Those accidents are real, and they are mostly made by people, not by rock. On the gym wall the usual injuries are quieter — a finger pulley that gives way, or an ankle turned landing from a boulder problem onto a mat.
This article follows the series format: what climbers actually injure, where the risk concentrates, what has been measured to reduce it, and why the answer is not to stay on the ground.
What actually gets injured
Injury rates depend heavily on how they are counted. The gym study counted only acute injuries serious enough to be reported. Surveys that also count overuse injuries find much higher figures: a Swedish study of 606 climbers found 4.2 injuries per 1,000 climbing hours, and 93% of those were overuse. A critical review of eight studies of sport climbing and bouldering put the average at 2.71 per 1,000 hours, with a wide spread. A larger review of more than 400 studies concluded that bouldering, sport and indoor climbing have a small injury rate, minor severity and few deaths, while alpine and ice climbing rank higher on all three.
Climbing injury rates
Injuries per 1,000 hours of climbing in three kinds of study.
Source: Schöffl, Hoffmann and Küpper, Wilderness and Environmental Medicine 24(3):187–194 (2013); Jones, Schöffl and Johnson (2018); Backe et al., Scandinavian Journal of Medicine and Science in Sports (2009).
The fingers take the brunt of it. In a series of 604 injured climbers, 20% had pulley injuries, 122 cases, of which 74 were ruptures. The pulleys are bands that hold the finger tendons against the bone, and the one at the base of the ring finger, the A2, is the most often injured. At the first British Open competition, 26% of 67 climbers showed signs of a previous A2 injury. A 2026 scoping review of 45 studies found pulley injuries frequent in both sport climbing and bouldering, and ankle sprains common in bouldering.
Finger pulley injuries
How often climbers injure the pulleys that hold the finger tendons.
Source: Schöffl et al., Wilderness and Environmental Medicine (2003); Bollen and Gunson, British Journal of Sports Medicine 24(1):16 (1990).
Emergency departments see the acute end. From 1990 to 2007, US emergency departments treated an estimated 40,282 climbing injuries, more than half among people aged 20 to 39. From 2014 to 2023 the estimate rose to 47,251. Falls caused 58.8% and fractures made up 26.8%; falls from more than 20 feet carried higher odds of fracture, and 9% of patients were admitted.
Climbing injuries in US emergency departments
Estimated national totals from the NEISS surveillance system.
Source: Nelson and McKenzie, Am J Prev Med (2009); Buzzacott et al., Wilderness Environ Med (2018); Lin et al., JBJS Open Access (2026).
The annual count has roughly doubled as the sport has grown. From 2008 to 2016 the mean was about 3,800 injuries a year; an analysis of 2010 to 2019 found annual estimates rising from 2,381 to 4,596. The ankle was the most commonly fractured site, accounting for 27% of fractures in the 2008 to 2016 data, and lower limbs made up 47% of all injuries. None of those figures is a rate, because nobody counts how many hours Americans spend climbing. They show that more people are climbing, and that when they are hurt, it is usually a fall and usually a leg.
When the risk concentrates
Bouldering carries most of the gym injuries. The German Alpine Club’s 2025 statistics on gym accidents analysed 252 cases: 174 were bouldering, 69%, and 68 were roped climbing. Lower limbs made up 46% of bouldering injuries, with ankle sprains the commonest single injury. Bouldering also raised the risk of a first injury in the Swedish study.

The reason is the fall itself. In a 2025 study of 245 injured boulderers with 301 injuries, 67% were to the legs and 28% were ankle sprains. Eighty-five per cent of the falls were involuntary, about three quarters landed feet first, and 47% came from the top section of the wall. A roped climber who falls is caught by the rope; a boulderer falls all the way to the mat, and a mat does not help much when a foot lands on its edge or on another climber. Emergency data point the same way: ankle injuries were 2.25 times more likely indoors than outdoors in a US analysis of 2010 to 2019.
Serious and fatal accidents concentrate outside, and on the rope system. In Austria from 2005 to 2018 there were 2,992 climbing rescue incidents, with a case fatality rate of 4.7%; most deaths involved multiple trauma or head injury, and belay errors caused 138 injuries. The American Alpine Club, which has published accident reports since 1948, says rappelling errors, poor route-finding on the descent and slips on exposed ground account for nearly 30% of serious incidents in some years, and that 43% of accidents since 1948 involved experienced climbers. Lowering accidents, including ropes too short to reach the ground, rose from six in 2016 to twelve in 2018.
Where serious climbing accidents come from
Austrian climbing rescues, 2005–2018, and gym accident statistics.
Source: Rugg et al., International Journal of Environmental Research and Public Health 17(20):7596 (2020); German Alpine Club gym accident statistics 2025, via Lacrux (2026).
What has been measured to work
There are no randomised trials of climbing injury prevention. A 2015 systematic review found 19 studies covering 35 risk factors or prevention measures, almost all observational. What there is comes from accident analysis, and it points consistently at the same few things.
Helmets are the clearest. In the Austrian rescue data, climbers without a helmet had 1.81 times the odds of severe or fatal injury, and in a Yosemite series of 220 injured climbers, 12 of 13 deaths were from head injury or hypothermia. Checks are next. The German Alpine Club’s 2025 report found that partner checks and self-checks were not done consistently, and its one death that year was a climber using an auto-belay who was not clipped in and fell to the ground. The American Alpine Club’s own reports turn again and again on the same small failures: a knot not finished, a rope end not knotted, a miscommunication about being off belay.
For fingers, the evidence is thinner. The Swedish study found that 93% of injuries were overuse, and that bouldering and being overweight raised the risk of a first injury; no trial has tested a way to prevent pulley damage. What follows from overuse is the general rule of this series: increase difficulty and training volume gradually, and have persistent finger pain assessed rather than climbed through. In bouldering, falls are the mechanism, so the practical measures are climbing down rather than jumping, falling on to the whole mat, keeping the landing zone clear of other people and resting before the top moves when tired. None of these has been tested in a trial; all of them follow directly from where the measured injuries come from.
Why the answer is not to stay on the ground
Climbing has something unusual in this series: randomised trials of benefit. German researchers have tested bouldering as a treatment for depression. In a multicentre trial of 133 people, depression scores fell by 8.4 points with bouldering therapy against 3.0 with a home exercise programme, an effect size of 0.55. A later trial of 156 patients found bouldering therapy was not inferior to group cognitive behavioural therapy. A 2025 systematic review of seven studies and 471 participants found bouldering combined with mindfulness lowered depression scores by about 8.3 points, from moderate to mild, with no adverse events reported.
Bouldering as depression therapy
Randomised trials of bouldering psychotherapy, change in depression score.
Source: Karg et al., BMC Psychiatry (2020); Larsson, Larsson and Nordeman, BMC Psychiatry, doi:10.1186/s12888-025-07292-3 (2025); Luttenberger et al., British Journal of Clinical Psychology (2022).

Those trials were run as therapy, with trained staff and small groups, so their results say most about structured programmes rather than casual climbing. They do show that the activity itself can be prescribed safely: across the review’s studies, no adverse events were reported. Set that against an acute injury rate in gyms of 0.02 per 1,000 hours and overuse injuries that are common but mostly minor, and the balance for most recreational climbers is clearly positive.
The risks that remain are concentrated and specific: fingers loaded too hard too soon, ankles landing badly from a boulder problem, and on real rock the rope system failing through a missed check. Each has a known answer — progression, controlled falls and down-climbing, helmets and partner checks. The answer is to climb carefully, not to stop climbing.
Questions people ask
Is indoor climbing dangerous?
Acute injuries are rare: one gym recorded 0.02 per 1,000 hours. Overuse injuries, especially to fingers, are more common but usually minor.
Is bouldering safer than roped climbing?
Not for ankles. Bouldering accounted for 69% of gym accidents in one German analysis, mostly from falls onto mats.
What is a climbing pulley injury?
Damage to the bands that hold finger tendons in place, most often the A2 pulley of the ring finger. It accounted for about a fifth of injuries in one large series.
Should I wear a helmet when climbing outdoors?
Yes. In Austrian rescue data, climbers without helmets had 1.81 times the odds of severe or fatal injury.
Can climbing help with depression?
Randomised trials of structured bouldering therapy found meaningful reductions in depression scores. It should complement, not replace, treatment from a clinician.
The short version
- A climbing gym recorded 0.02 acute injuries per 1,000 hours; counting overuse raises the rate to 2 to 4.
- Finger pulley injuries make up about a fifth of climbing injuries; most are overuse.
- Bouldering causes most gym accidents, mainly ankles from falls onto mats.
- Serious accidents outdoors turn on the rope system and on helmets: no helmet, 1.81 times the odds of severe injury.
- There are no prevention trials; checks, progression and controlled falls follow from the accident data.
- Bouldering therapy lowered depression scores in randomised trials.
This is a summary of published research, not medical or climbing instruction. It does not replace training from a qualified instructor or assessment of an injury by a doctor or physiotherapist. If you are being treated for depression, talk to your clinician before changing treatment.
Further reading: Schöffl et al., Sports Medicine 40(8):657–679 (2010), for a review of injury risk across climbing disciplines. Rugg et al., International Journal of Environmental Research and Public Health 17(20):7596 (2020), for Austrian rescue data. The American Alpine Club’s annual Accidents in North American Climbing.
- The Comfort of Crows, Margaret Renkl (2023). A year of small observations outdoors. Not about climbing, but a good companion to the evidence that time spent in an absorbing physical activity changes mood.
- Tomorrowmind, Gabriella Rosen Kellerman and Martin Seligman (2023). On resilience and mental fitness at work and beyond; relevant background to why structured activities like bouldering therapy help.
- The Unaccountability Machine, Dan Davies (2024). On how systems fail when no single person is responsible — a fair description of a missed partner check or a rope that stops short.
Sources
Schöffl V, Hoffmann G, Küpper T. Wilderness and Environmental Medicine 24(3):187–194 (2013). — Backe S, Ericson L, Janson S, Timpka T. Scandinavian Journal of Medicine and Science in Sports, doi:10.1111/j.1600-0838.2008.00851.x (2009). — Jones G, Schöffl V, Johnson MI. Critical review of climbing injury incidence (2018). — Schöffl V, et al. Sports Medicine 40(8):657–679 (2010). — Woollings KY, McKay CD, Emery CA. British Journal of Sports Medicine 49:1094–1099 (2015). — Schöffl V, et al. Pulley injuries in rock climbers. Wilderness and Environmental Medicine (2003). — Kubiak EN, et al. Bulletin of the NYU Hospital for Joint Diseases (2006). — Bollen S, Gunson C. British Journal of Sports Medicine 24(1):16 (1990). — Vagy J, et al. BMJ Open Sport and Exercise Medicine 12(1):e002830 (2026). — Beurienne et al. Frontiers in Sports and Active Living, doi:10.3389/fspor.2025.1609133 (2025). — Nelson NG, McKenzie LB. American Journal of Preventive Medicine, doi:10.1016/j.amepre.2009.04.025 (2009). — Buzzacott P, Schöffl I, Chimiak JM, Schöffl V. Wilderness and Environmental Medicine (2018). — Sabbagh RS, et al. Journal of Sports Medicine and Physical Fitness (2021). — Lin J, et al. JBJS Open Access, doi:10.2106/JBJS.OA.25.00137 (2026). — Rugg C, et al. International Journal of Environmental Research and Public Health 17(20):7596 (2020). — American Alpine Club, Accidents in North American Climbing; Know the Ropes: Human Factors. — REI Uncommon Path, citing ANAC (September 2018). — Bowie WS, et al. Western Journal of Medicine (1988). — German Alpine Club (DAV) gym accident statistics 2025, reported by Lacrux (22 August 2026). — Karg N, Dorscht L, Kornhuber J, Luttenberger K. BMC Psychiatry, doi:10.1186/s12888-020-02518-y (2020). — Luttenberger K, et al. British Journal of Clinical Psychology, doi:10.1111/bjc.12347 (2022). — Larsson R, Larsson A, Nordeman L. BMC Psychiatry, doi:10.1186/s12888-025-07292-3 (2025).